Written by GFFI Team
The Spine’s Sections Are Defined by Their Vertebrae.
It is common to split spinal anatomy into four primary divisions, each with a different number of vertebrae (the spherical bones that form the backbone’s structure). Vertebrae, or vertebral bodies, are also referred to as vertebrates.
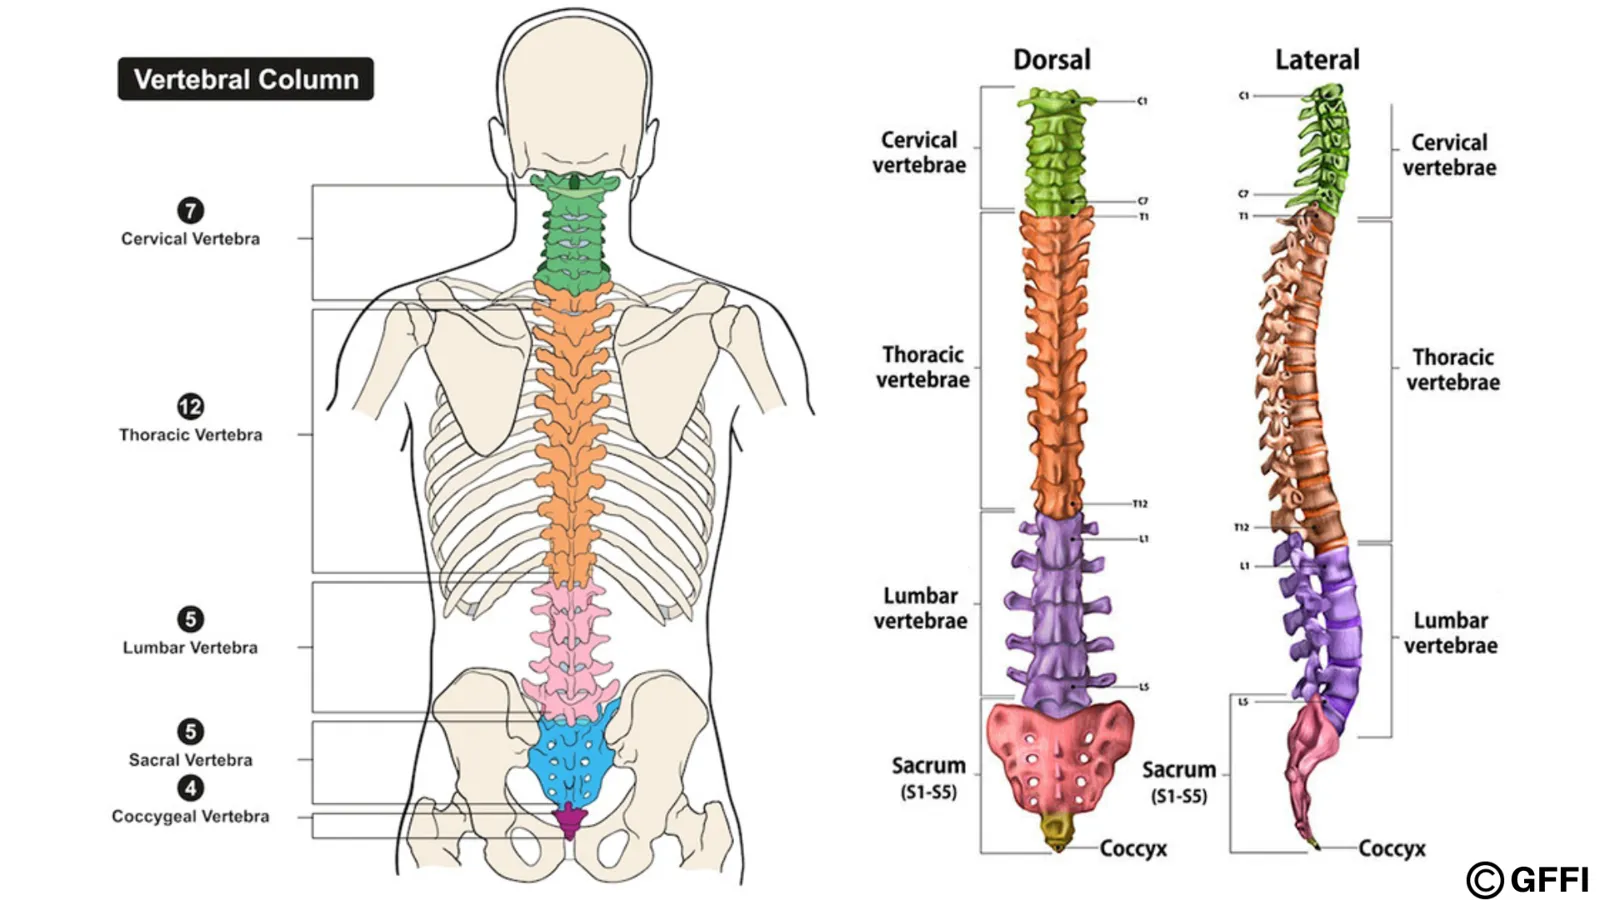
The cervical spine (neck) consists of seven cervical vertebrae (C1 to C7), with C1 at the top of the spine and C7 at the bottom of the spine. If you have a neck condition, you may have neck discomfort, as well as pain that extends down your arms to your hands and fingers.
There are 12 thoracic vertebrae (known as T1 to T12) in the thoracic spine, which are linked to the ribs and the sternum and form the upper back (breast bone). The ribs and sternum provide excellent support for this portion of the spine, making it relatively stable and less prone to injury while moving.
There are five vertebrae in the lumbar spine (L1 to L5), all of which may move and bend quite a little. Because this part of the spine carries the greatest weight and allows for the most mobility (which strains the anatomical components), this is the area that is most often connected with back pain. Leg and foot discomfort might be caused by issues with the low back.
Sacrum (bottom of the spine) is a triangular-shaped bone that acts as the spine’s base and forms a portion of the pelvis.
L5-S1 is an area of the lumbar spine that is particularly vulnerable to degeneration and back pain. Four tiny bones that protrude from the sacrum form the coccyx, or tailbone (the tailbone at the very bottom of the spine).
Spinal biomechanics in the lower back’s spinal motion segment
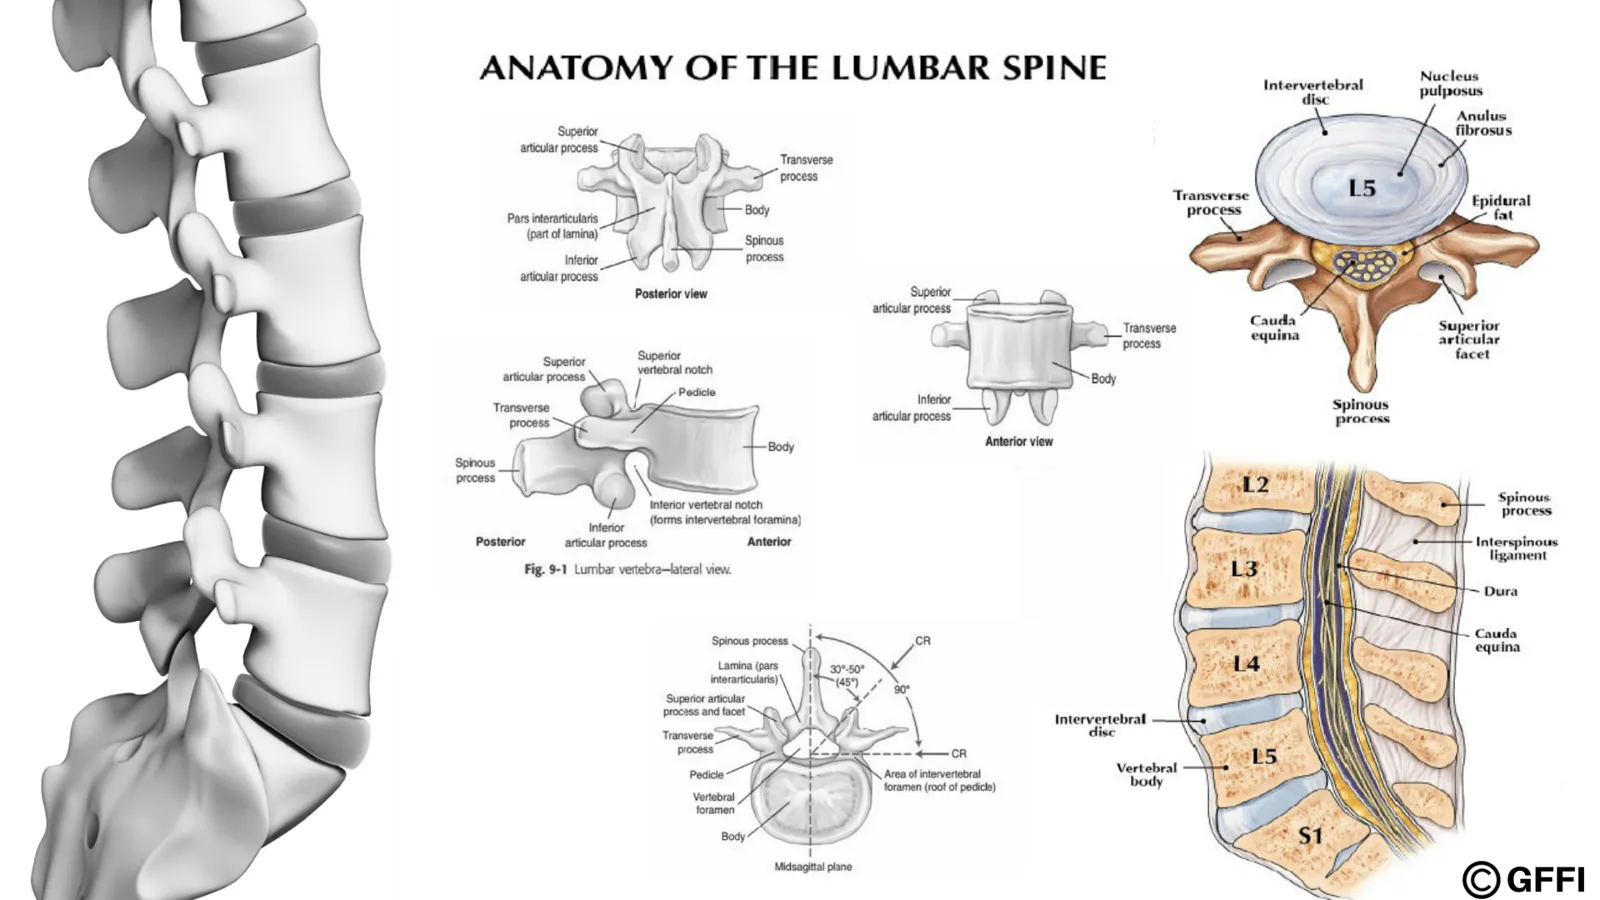
The lumbar spine and sacral spine meet at the L5-S1 spinal motion segment, which is also known as the lumbosacral joint. Here, the spine’s curvature shifts from forward-curving to backward-curving (backward curve). Legs and pelvis are supported by L5-S1’s ability to transmit stresses from the spine.
Because of its unique architecture and greater mechanical stress and stresses than the preceding segments, the L5-S1 motion segment is more often injured. Traumatic injuries, degeneration, disc herniation, and/or nerve discomfort may occur because of these traits.
The L5-S1 Joint Frequently Facing Issues
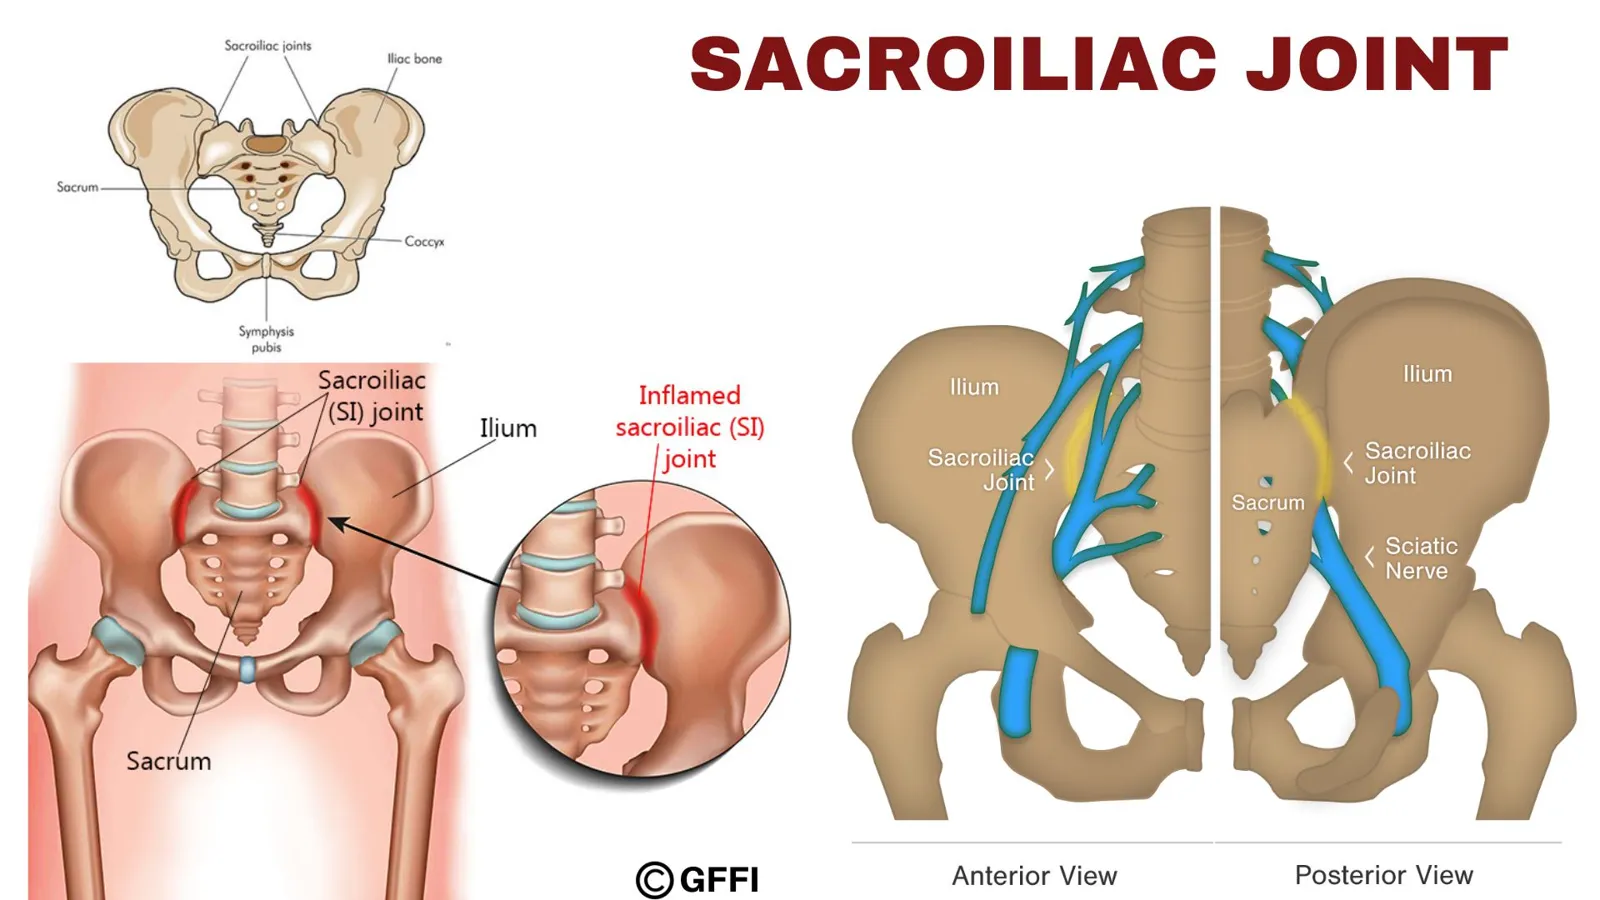
L5-S1 is often susceptible to excessive biomechanical stress, resulting in additional stresses and an increased risk of injury.. There are a number of common issues, including
Discs Problem: There are issues with the discs. L5-S1 is a common location for disc herniation in the lower back. This disc has a steeper slope, which increases the risk of damage and degeneration due to increased shear forces.
Facet Joint issue: Pain in the facet joints. Wear-and-tear arthritis (osteoarthritis) may develop in the lumbosacral joint owing to its high load-bearing capacity. Inflammatory disorders, such as rheumatoid arthritis or degenerative spondylolisthesis, may also cause facet joint discomfort.
Spondylolysis. Repetitive stress may cause spondylolysis, which is the fracture of pars interarticularis (a tiny bone fragment that connects the facet joints of the vertebral arch) in the L5 vertebra. It may happen on either side of the aisle. Pars stress response is a situation where the bone does not shatter but is strained, and this is referred to as a pars stress reaction.
Spondylolisthesis. Spondylolisthesis occurs when the L5 pars fracture on both sides, causing the vertebra to slide across S1. Spondylolisthesis of L5 is most typically induced by repeated stress on the pars interarticularis and is most frequently observed in children and teenagers.. A fracture of the pars femoris owing to trauma is very rare.
Pain in the Sciatic Nerve and the SI Joint: The Root Causes
It might be difficult to identify the specific source of a patient’s discomfort. Back pain may be caused by nerve compression in the spine, as well as SI joint dysfunction.
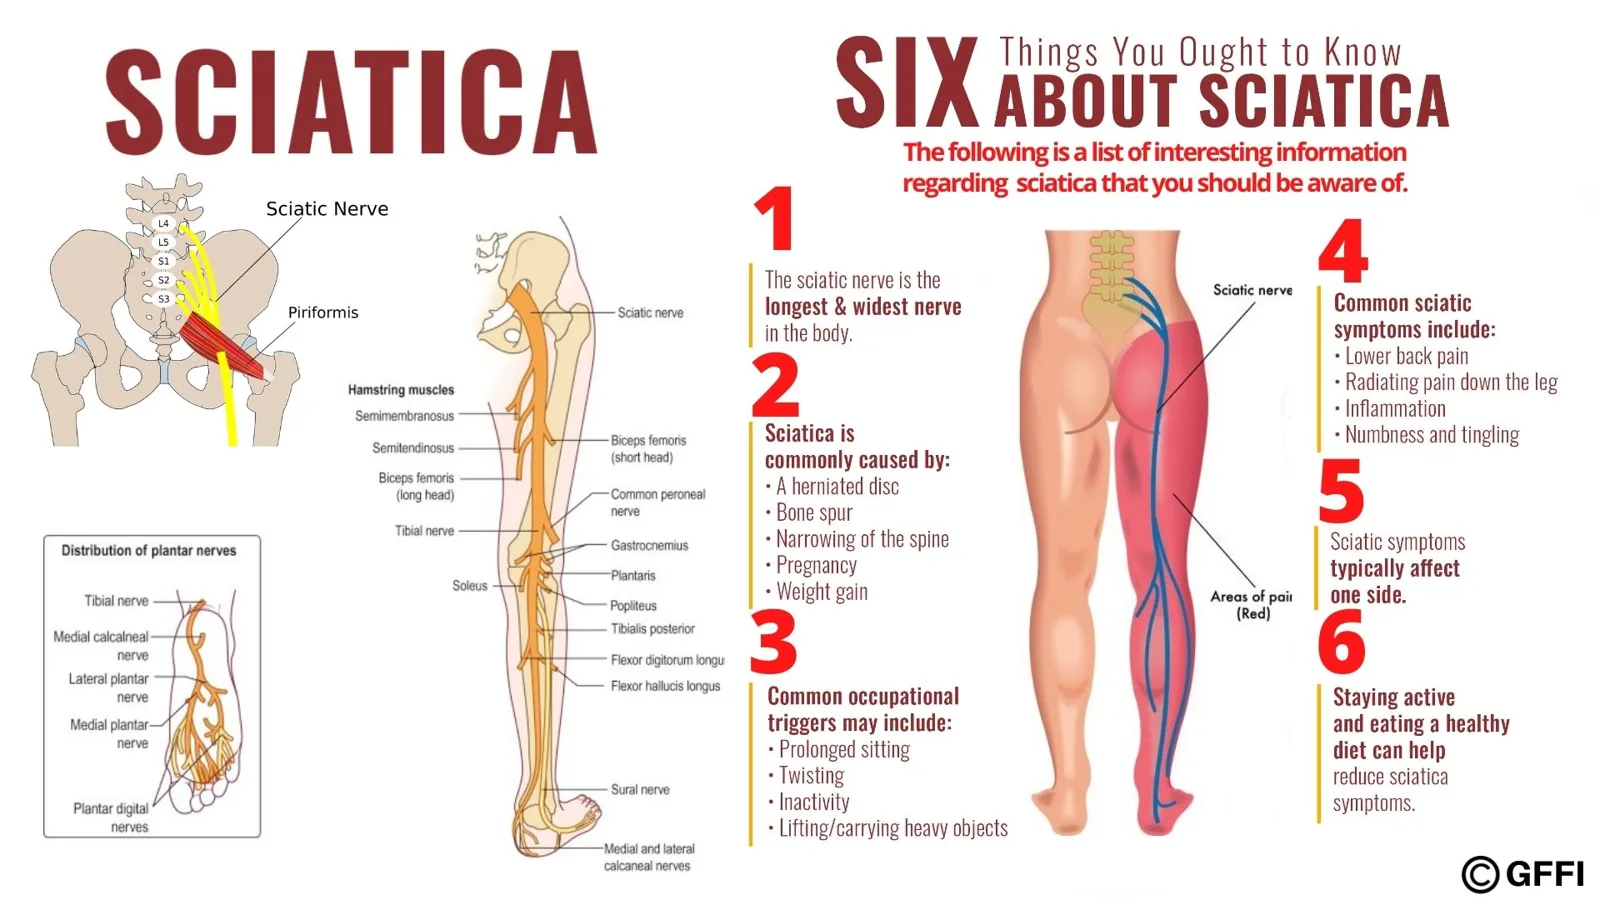
Problems with the spine that may lead to sciatica
1. A disc bulge, rupture, or herniation.
2. Spinal stenosis, which is the narrowing of the central canal of the spine,
3. This is a condition in which the holes where nerves escape from your spine get narrowed.
4. When one of the vertebrae in the lower back slides forward, it is known as spondylolisthesis (or segmental instability).
5. A condition in which the cartilage between the facet joints at the back of the spine wears away, leading to facet arthropathy.
6. A wound or infection
7.Diseases caused by malnutrition and genetics (less common)
Potential Causes of SI Joint Dysfunction
1. Injuries to the SI joint that result from a fall, automobile accident, or childbirth are all examples of SI joint trauma.
2. Degenerative SI joint
It is possible for both scenarios to be either acute (lasting less than a month) or chronic (lasting more than a month) (lasting a very long time).
It might take years for people with SI joint dysfunction to be diagnosed and treated for their pain, which can be debilitating.
When discomfort persists for more than a few weeks or has an effect on your everyday activities, you should consult a doctor at once.
Distinctive Therapies
Alternative and complementary medicine are terms used to describe non-medical therapies. “Alternative” doesn’t always suggest inferiority, but rather a departure from what is considered “conventional” in western medicine.
Alternate therapies for low back pain have been shown to help many people. Among the most common choices are:
Manual manipulation. Physical adjustments to the spine are made by a chiropractor or other healthcare practitioner in order to improve mobility and reduce stiffness, discomfort, or pain. It is done by using hand thrusts of variable speed and power. Some people’s low back discomfort has been relieved by manual manipulation.
Acupuncture. Acupuncture is based on traditional Chinese medicine and uses sites on the body that are supposed to rectify the body’s “qi,” or life energy. Proper qi is said to alleviate pain and suffering in the body, according to Chinese medicine. For nearly an hour, tiny needles are inserted into the skin. It’s been established that acupuncture may significantly reduce pain in certain patients.
Therapeutic massage. Massage treatment for the low back helps ease the muscular spasms that cause low back discomfort. Low-back pain may be alleviated by increasing blood flow, which brings nutrients and oxygen to the area to aid recovery.
Mindful meditation: Meditation in a calm and collected manner. Meditation may help alleviate the symptoms of chronic pain, such as sadness, anxiety, and sleep disturbances. Meditative treatments for pain relief encompass anything from deep breathing exercises to shifting one’s concentration away from the discomfort.
Links of Some of the research on disc degeneration related to back pain
- Low Back Pain: A Biomechanical Rationale Based on “Patterns” of Disc Degeneration.Von Forell GA, et al. Spine (Phila Pa 1976). 2015. PMID: 25996532
- Obesity is associated with reduced disc height in the lumbar spine but not at the lumbosacral junction.Urquhart DM, et al. Spine (Phila Pa 1976). 2014. PMID: 24825160
- [Advances in the study of anatomy and biomechanics of lumbosacral transitional vertebrae].Huang QQ, et al. Zhonghua Wai Ke Za Zhi. 2019. PMID: 30704219 Review. Chinese.
- Influence of age on the development of pathology.Sizer PS, et al. Curr Rev Pain. 2000.PMID: 10998745 Review.
- The segment-dependent changes in lumbar intervertebral …
GFFI टीम द्वारा लिखित
मेरुदंड के खंडों को उनकी कशेरुकाओं (vertebrae) द्वारा परिभाषित किया जाता है।
मेरुदंड की शारीरिक रचना को चार प्राथमिक भागों में विभाजित करना सामान्य है, जिनमें से प्रत्येक में कशेरुकाओं (वे गोलाकार अस्थियाँ जो रीढ़ की संरचना बनाती हैं) की संख्या भिन्न होती है। कशेरुकाओं, अथवा कशेरुका-काय (vertebral bodies), को वर्टिब्रेट्स भी कहा जाता है।
ग्रीवा मेरुदंड (cervical spine — गर्दन) में सात ग्रीवा कशेरुकाएँ (C1 से C7) होती हैं, जिनमें C1 मेरुदंड के शीर्ष पर और C7 तल पर स्थित होती है। यदि आपको गर्दन संबंधी कोई समस्या है, तो आपको गर्दन में असुविधा के साथ-साथ ऐसा दर्द भी हो सकता है जो आपकी भुजाओं से होते हुए हाथों और उंगलियों तक फैलता है।
वक्षीय मेरुदंड (thoracic spine) में 12 वक्षीय कशेरुकाएँ (T1 से T12) होती हैं, जो पसलियों और उरोस्थि (स्टर्नम — breast bone) से जुड़ी होती हैं और ऊपरी पीठ का निर्माण करती हैं। पसलियाँ और उरोस्थि मेरुदंड के इस भाग को उत्कृष्ट सहारा प्रदान करती हैं, जिससे यह अपेक्षाकृत स्थिर रहता है और गति के दौरान चोट के प्रति कम प्रवृत्त होता है।
कटि मेरुदंड (lumbar spine) में पाँच कशेरुकाएँ (L1 से L5) होती हैं, जो सभी काफ़ी हद तक गति कर सकती हैं और मुड़ सकती हैं। चूँकि मेरुदंड का यह भाग सर्वाधिक भार वहन करता है और सर्वाधिक गतिशीलता प्रदान करता है (जो शारीरिक घटकों पर तनाव डालता है), इसलिए यही वह क्षेत्र है जिसे प्रायः पीठ दर्द से जोड़ा जाता है। निचली पीठ की समस्याओं के कारण पैर और पाँव में असुविधा हो सकती है।
त्रिकास्थि (सेक्रम — मेरुदंड का निचला भाग) एक त्रिकोणाकार अस्थि है जो मेरुदंड के आधार के रूप में कार्य करती है और श्रोणि (pelvis) का एक भाग बनाती है।
L5-S1 कटि मेरुदंड का वह क्षेत्र है जो अपक्षय (degeneration) और पीठ दर्द के प्रति विशेष रूप से संवेदनशील है। त्रिकास्थि से निकलने वाली चार छोटी अस्थियाँ अनुत्रिक (कॉक्सिक्स), अथवा पुच्छास्थि (tailbone — मेरुदंड के बिल्कुल निचले सिरे पर स्थित पुच्छास्थि) का निर्माण करती हैं।
निचली पीठ के मेरुदंडीय गति खंड (spinal motion segment) में मेरुदंडीय जैवयांत्रिकी
कटि मेरुदंड और त्रिक मेरुदंड L5-S1 मेरुदंडीय गति खंड पर मिलते हैं, जिसे लम्बोसेक्रल संधि (lumbosacral joint) भी कहा जाता है। यहाँ मेरुदंड की वक्रता आगे की ओर मुड़ने से पीछे की ओर मुड़ने (पश्च वक्र) में परिवर्तित होती है। मेरुदंड से तनावों को संचारित करने की L5-S1 की क्षमता द्वारा पैरों और श्रोणि को सहारा मिलता है।
अपनी विशिष्ट संरचना तथा ऊपर स्थित खंडों की तुलना में अधिक यांत्रिक तनाव और दबावों के कारण, L5-S1 गति खंड अधिक बार चोटिल होता है। इन विशेषताओं के कारण आघातजन्य चोटें, अपक्षय, डिस्क हर्निएशन, और/अथवा तंत्रिका संबंधी असुविधा हो सकती है।
L5-S1 संधि में प्रायः आने वाली समस्याएँ
L5-S1 प्रायः अत्यधिक जैवयांत्रिक तनाव के प्रति संवेदनशील होती है, जिसके परिणामस्वरूप अतिरिक्त तनाव और चोट का बढ़ा हुआ जोखिम उत्पन्न होता है.. कई सामान्य समस्याएँ हैं, जिनमें सम्मिलित हैं
डिस्क संबंधी समस्या: डिस्कों में समस्याएँ होती हैं। L5-S1 निचली पीठ में डिस्क हर्निएशन का एक सामान्य स्थल है। इस डिस्क का ढलान अधिक तीव्र होता है, जो बढ़े हुए अपरूपण बलों (shear forces) के कारण क्षति और अपक्षय के जोखिम को बढ़ाता है।
फ़ैसेट संधि समस्या: फ़ैसेट संधियों (facet joints) में दर्द। उच्च भार-वहन क्षमता के कारण लम्बोसेक्रल संधि में घिसाव-जनित संधिशोथ (ऑस्टियोआर्थराइटिस) विकसित हो सकता है। रूमेटॉइड आर्थराइटिस या डीजेनरेटिव स्पॉन्डिलोलिस्थेसिस जैसे सूजनकारी विकार भी फ़ैसेट संधि में असुविधा उत्पन्न कर सकते हैं।
स्पॉन्डिलोलिसिस (Spondylolysis)। बार-बार के तनाव से स्पॉन्डिलोलिसिस हो सकता है, जो L5 कशेरुका में पार्स इंटरआर्टिकुलैरिस (pars interarticularis — एक छोटा अस्थि-खंड जो कशेरुका-चाप की फ़ैसेट संधियों को जोड़ता है) का अस्थिभंग है। यह किसी भी ओर हो सकता है। पार्स तनाव प्रतिक्रिया वह स्थिति है जिसमें अस्थि टूटती नहीं, बल्कि तनावग्रस्त होती है, और इसे पार्स स्ट्रेस रिएक्शन (pars stress reaction) कहा जाता है।
स्पॉन्डिलोलिस्थेसिस (Spondylolisthesis)। स्पॉन्डिलोलिस्थेसिस तब होता है जब L5 पार्स दोनों ओर से अस्थिभंगित हो जाता है, जिससे कशेरुका S1 के ऊपर खिसक जाती है। L5 का स्पॉन्डिलोलिस्थेसिस प्रायः पार्स इंटरआर्टिकुलैरिस पर बार-बार के तनाव से उत्पन्न होता है और सर्वाधिक बार बच्चों और किशोरों में देखा जाता है.. आघात के कारण पार्स फ़ीमोरिस का अस्थिभंग अत्यंत दुर्लभ है।
साइटिक तंत्रिका और SI संधि में दर्द: मूल कारण
रोगी की असुविधा के विशिष्ट स्रोत की पहचान करना कठिन हो सकता है। पीठ दर्द मेरुदंड में तंत्रिका-संपीडन (nerve compression) के साथ-साथ SI संधि की दुष्क्रिया (dysfunction) के कारण भी हो सकता है।
मेरुदंड की वे समस्याएँ जो साइटिका (sciatica) का कारण बन सकती हैं
1. डिस्क का उभार, विदारण अथवा हर्निएशन।
2. स्पाइनल स्टेनोसिस, जो मेरुदंड की केंद्रीय नलिका का संकीर्ण होना है,
3. यह वह स्थिति है जिसमें वे छिद्र संकीर्ण हो जाते हैं जहाँ से तंत्रिकाएँ आपके मेरुदंड से बाहर निकलती हैं।
4. जब निचली पीठ की कोई कशेरुका आगे की ओर खिसक जाती है, तो इसे स्पॉन्डिलोलिस्थेसिस (अथवा खंडीय अस्थिरता — segmental instability) कहा जाता है।
5. वह स्थिति जिसमें मेरुदंड के पिछले भाग में फ़ैसेट संधियों के बीच की उपास्थि (cartilage) घिस जाती है, जिससे फ़ैसेट आर्थ्रोपैथी होती है।
6. कोई घाव अथवा संक्रमण
7.कुपोषण और आनुवंशिकी के कारण होने वाले रोग (कम सामान्य)
SI संधि दुष्क्रिया के संभावित कारण
1. गिरने, वाहन दुर्घटना अथवा प्रसव के परिणामस्वरूप SI संधि में होने वाली चोटें — ये सभी SI संधि आघात के उदाहरण हैं।
2. अपक्षयी (degenerative) SI संधि
दोनों परिस्थितियाँ तीव्र (एक महीने से कम समय तक रहने वाली) अथवा दीर्घकालिक (एक महीने से अधिक समय तक रहने वाली) (बहुत लंबे समय तक रहने वाली) हो सकती हैं।
SI संधि दुष्क्रिया से ग्रस्त लोगों के दर्द का निदान और उपचार होने में वर्षों लग सकते हैं, और यह दर्द अशक्तकारी हो सकता है।
जब असुविधा कुछ सप्ताहों से अधिक बनी रहे अथवा आपकी दैनिक गतिविधियों को प्रभावित करे, तो आपको तत्काल चिकित्सक से परामर्श करना चाहिए।
विशिष्ट चिकित्सा-पद्धतियाँ
वैकल्पिक और पूरक चिकित्सा वे पद हैं जिनका प्रयोग गैर-औषधीय चिकित्साओं का वर्णन करने के लिए किया जाता है। “वैकल्पिक” का अर्थ सदैव हीनता नहीं होता, बल्कि यह पाश्चात्य चिकित्सा में “पारंपरिक” मानी जाने वाली पद्धति से भिन्नता को दर्शाता है।
निचली पीठ के दर्द के लिए वैकल्पिक चिकित्साएँ अनेक लोगों के लिए सहायक सिद्ध हुई हैं। सबसे सामान्य विकल्पों में निम्नलिखित हैं:
मैनुअल मैनिपुलेशन (Manual manipulation)। गतिशीलता में सुधार करने और जकड़न, असुविधा या दर्द को कम करने के लिए किसी काइरोप्रैक्टर या अन्य स्वास्थ्य-सेवा चिकित्सक द्वारा मेरुदंड में शारीरिक समायोजन किए जाते हैं। यह परिवर्तनशील गति और शक्ति के हस्त-आघात (hand thrusts) द्वारा किया जाता है। कुछ लोगों की निचली पीठ की असुविधा मैनुअल मैनिपुलेशन से दूर हुई है।
एक्यूपंक्चर (Acupuncture)। एक्यूपंक्चर पारंपरिक चीनी चिकित्सा पर आधारित है और शरीर के उन स्थलों का उपयोग करता है जिनके बारे में माना जाता है कि वे शरीर की “ची” (qi), अथवा जीवन-ऊर्जा, को सुधारते हैं। चीनी चिकित्सा के अनुसार, उचित ची शरीर में दर्द और कष्ट को कम करती है। लगभग एक घंटे तक त्वचा में अत्यंत पतली सुइयाँ प्रविष्ट की जाती हैं। यह स्थापित हो चुका है कि एक्यूपंक्चर कुछ रोगियों में दर्द को उल्लेखनीय रूप से कम कर सकता है।
चिकित्सीय मालिश (Therapeutic massage)। निचली पीठ के लिए मालिश उपचार उन पेशीय ऐंठनों को शांत करने में सहायता करता है जो निचली पीठ में असुविधा का कारण बनती हैं। रक्त-प्रवाह बढ़ाकर, जो पुनर्प्राप्ति में सहायता हेतु उस क्षेत्र तक पोषक तत्व और ऑक्सीजन पहुँचाता है, निचली पीठ के दर्द को कम किया जा सकता है।
सचेतन ध्यान (Mindful meditation): शांत और संयमित ढंग से किया जाने वाला ध्यान। ध्यान दीर्घकालिक दर्द के लक्षणों, जैसे उदासी, चिंता और निद्रा-विकारों, को कम करने में सहायक हो सकता है। दर्द-निवारण हेतु ध्यान-आधारित उपचारों में गहरी श्वास के अभ्यास से लेकर असुविधा से अपना ध्यान हटाने तक सब कुछ सम्मिलित है।
पीठ दर्द से संबंधित डिस्क अपक्षय पर कुछ शोध-कार्यों के लिंक
- Low Back Pain: A Biomechanical Rationale Based on “Patterns” of Disc Degeneration.Von Forell GA, et al. Spine (Phila Pa 1976). 2015. PMID: 25996532
- Obesity is associated with reduced disc height in the lumbar spine but not at the lumbosacral junction.Urquhart DM, et al. Spine (Phila Pa 1976). 2014. PMID: 24825160
- [Advances in the study of anatomy and biomechanics of lumbosacral transitional vertebrae].Huang QQ, et al. Zhonghua Wai Ke Za Zhi. 2019. PMID: 30704219 Review. Chinese.
- Influence of age on the development of pathology.Sizer PS, et al. Curr Rev Pain. 2000.PMID: 10998745 Review.
- The segment-dependent changes in lumbar intervertebral …
Escrito por el equipo de GFFI
Las secciones de la columna vertebral se definen por sus vértebras.
Es habitual dividir la anatomía de la columna en cuatro regiones principales, cada una con un número distinto de vértebras (los huesos redondeados que forman la estructura del raquis). Las vértebras, o cuerpos vertebrales, también se denominan segmentos vertebrales.
La columna cervical (cuello) consta de siete vértebras cervicales (C1 a C7), con C1 en la parte superior de la columna y C7 en la parte inferior. Si usted padece una afección cervical, puede presentar molestias en el cuello, así como dolor que se irradia por los brazos hasta las manos y los dedos.
La columna torácica cuenta con 12 vértebras torácicas (denominadas T1 a T12), que están unidas a las costillas y al esternón y forman la parte superior de la espalda. Las costillas y el esternón (hueso del pecho) proporcionan un soporte excelente a esta porción de la columna, lo que la hace relativamente estable y menos propensa a lesionarse durante el movimiento.
La columna lumbar tiene cinco vértebras (L1 a L5), todas ellas con una considerable capacidad de movimiento y flexión. Dado que esta parte de la columna soporta el mayor peso y permite la mayor movilidad (lo que somete a tensión a los componentes anatómicos), es la región que con mayor frecuencia se asocia al dolor de espalda. Los problemas de la zona lumbar pueden provocar molestias en las piernas y los pies.
El sacro (parte inferior de la columna) es un hueso de forma triangular que actúa como base de la columna y forma parte de la pelvis.
L5-S1 es una región de la columna lumbar especialmente vulnerable a la degeneración y al dolor de espalda. Cuatro pequeños huesos que se proyectan desde el sacro forman el cóccix, o rabadilla (el hueso situado en el extremo inferior de la columna).
Biomecánica vertebral en el segmento de movimiento espinal de la zona lumbar
La columna lumbar y la columna sacra se unen en el segmento de movimiento espinal L5-S1, también conocido como articulación lumbosacra. En este punto, la curvatura de la columna cambia de convexa hacia delante a convexa hacia atrás (curva posterior). Las piernas y la pelvis reciben soporte gracias a la capacidad de L5-S1 para transmitir las cargas procedentes de la columna.
Debido a su arquitectura singular y a una tensión y unas cargas mecánicas mayores que las de los segmentos superiores, el segmento de movimiento L5-S1 se lesiona con mayor frecuencia. Estas características pueden dar lugar a lesiones traumáticas, degeneración, hernia discal o molestias de origen nervioso.
Problemas frecuentes de la articulación L5-S1
L5-S1 es a menudo susceptible a una tensión biomecánica excesiva, lo que genera cargas adicionales y un mayor riesgo de lesión.. Existen varios problemas frecuentes, entre ellos
Problemas discales: existen alteraciones en los discos. L5-S1 es una localización habitual de hernia discal en la zona lumbar. Este disco presenta una inclinación más pronunciada, lo que aumenta el riesgo de daño y degeneración debido al incremento de las fuerzas de cizallamiento.
Problemas de las articulaciones facetarias: dolor en las articulaciones facetarias. La artrosis por desgaste (osteoartritis) puede desarrollarse en la articulación lumbosacra debido a su elevada capacidad de soporte de carga. Los trastornos inflamatorios, como la artritis reumatoide, o la espondilolistesis degenerativa también pueden provocar molestias en las articulaciones facetarias.
Espondilólisis. La tensión repetitiva puede causar espondilólisis, que es la fractura de la pars interarticularis (un pequeño fragmento óseo que conecta las articulaciones facetarias del arco vertebral) en la vértebra L5. Puede producirse en cualquiera de los dos lados. La respuesta de estrés de la pars es una situación en la que el hueso no se fractura pero está sometido a tensión, y se denomina reacción de estrés de la pars.
Espondilolistesis. La espondilolistesis se produce cuando la pars de L5 se fractura en ambos lados, lo que provoca que la vértebra se deslice sobre S1. La espondilolistesis de L5 se debe con mayor frecuencia a la tensión repetida sobre la pars interarticularis y se observa sobre todo en niños y adolescentes.. Una fractura de la pars femoris de origen traumático es muy poco frecuente.
Dolor del nervio ciático y de la articulación sacroilíaca (SI): causas de fondo
Puede resultar difícil identificar la fuente específica de las molestias de un paciente. El dolor de espalda puede deberse a la compresión nerviosa en la columna, así como a la disfunción de la articulación SI.
Problemas de la columna que pueden provocar ciática
1. Una protrusión, rotura o hernia discal.
2. Estenosis espinal, que es el estrechamiento del conducto central de la columna,
3. Una afección en la que se estrechan los orificios por los que los nervios salen de la columna.
4. Cuando una de las vértebras de la zona lumbar se desliza hacia delante, se denomina espondilolistesis (o inestabilidad segmentaria).
5. Una afección en la que el cartílago entre las articulaciones facetarias de la parte posterior de la columna se desgasta, lo que conduce a una artropatía facetaria.
6. Una herida o infección
7.Enfermedades causadas por la malnutrición y la genética (menos frecuentes)
Posibles causas de la disfunción de la articulación SI
1. Las lesiones de la articulación SI derivadas de una caída, un accidente de tráfico o el parto son ejemplos de traumatismo de la articulación SI.
2. Articulación SI degenerativa
Ambos escenarios pueden ser agudos (con una duración inferior a un mes) o crónicos (con una duración superior a un mes) (prolongándose durante mucho tiempo).
Las personas con disfunción de la articulación SI pueden tardar años en recibir un diagnóstico y tratamiento para su dolor, que puede llegar a ser incapacitante.
Cuando las molestias persistan durante más de unas semanas o afecten a sus actividades cotidianas, debe consultar a un médico de inmediato.
Terapias distintivas
Los términos medicina alternativa y complementaria se utilizan para describir terapias no médicas. “Alternativa” no implica necesariamente inferioridad, sino más bien un alejamiento de lo que se considera “convencional” en la medicina occidental.
Se ha demostrado que las terapias alternativas para el dolor lumbar ayudan a muchas personas. Entre las opciones más comunes se encuentran:
Manipulación manual. Un quiropráctico u otro profesional sanitario realiza ajustes físicos en la columna con el fin de mejorar la movilidad y reducir la rigidez, las molestias o el dolor. Se lleva a cabo mediante impulsos manuales de velocidad y potencia variables. La manipulación manual ha aliviado las molestias lumbares de algunas personas.
Acupuntura. La acupuntura se basa en la medicina tradicional china y utiliza puntos del cuerpo que, supuestamente, corrigen el “qi”, o energía vital, del organismo. Según la medicina china, un qi adecuado alivia el dolor y el sufrimiento del cuerpo. Se insertan agujas muy finas en la piel durante casi una hora. Se ha establecido que la acupuntura puede reducir significativamente el dolor en determinados pacientes.
Masaje terapéutico. El masaje de la zona lumbar ayuda a aliviar los espasmos musculares que causan molestias lumbares. El dolor lumbar puede atenuarse al aumentar el flujo sanguíneo, que aporta nutrientes y oxígeno a la zona para favorecer la recuperación.
Meditación consciente (mindfulness): meditación practicada de manera serena y centrada. La meditación puede ayudar a aliviar síntomas asociados al dolor crónico, como la tristeza, la ansiedad y las alteraciones del sueño. Los tratamientos meditativos para el alivio del dolor abarcan desde ejercicios de respiración profunda hasta desviar la atención de las molestias.
Enlaces a algunas investigaciones sobre la degeneración discal relacionada con el dolor de espalda
- Low Back Pain: A Biomechanical Rationale Based on “Patterns” of Disc Degeneration.Von Forell GA, et al. Spine (Phila Pa 1976). 2015. PMID: 25996532
- Obesity is associated with reduced disc height in the lumbar spine but not at the lumbosacral junction.Urquhart DM, et al. Spine (Phila Pa 1976). 2014. PMID: 24825160
- [Advances in the study of anatomy and biomechanics of lumbosacral transitional vertebrae].Huang QQ, et al. Zhonghua Wai Ke Za Zhi. 2019. PMID: 30704219 Review. Chinese.
- Influence of age on the development of pathology.Sizer PS, et al. Curr Rev Pain. 2000.PMID: 10998745 Review.
- The segment-dependent changes in lumbar intervertebral …
كتبه فريق GFFI
تتحدّد أقسام العمود الفقري بفقراتها.
من الشائع تقسيم تشريح العمود الفقري إلى أربعة أقسام رئيسية، يضم كلٌّ منها عددًا مختلفًا من الفقرات (العظام الكروية التي تُشكّل بنية العمود الفقري). ويُشار إلى الفقرات، أو أجسام الفقرات (vertebral bodies)، أيضًا باسم الفقاريات.
يتألف العمود الفقري العنقي (الرقبة) من سبع فقرات عنقية (من C1 إلى C7)، تقع C1 في أعلى العمود الفقري وC7 في أسفله. وإذا كنت تعاني من حالة في الرقبة، فقد تشعر بانزعاج في الرقبة، إضافةً إلى ألم يمتد عبر ذراعيك إلى يديك وأصابعك.
يضم العمود الفقري الصدري 12 فقرة صدرية (تُعرف بـ T1 إلى T12)، ترتبط بالأضلاع وعظم القص، وتُشكّل أعلى الظهر (عظم الصدر). وتوفر الأضلاع وعظم القص دعمًا ممتازًا لهذا الجزء من العمود الفقري، مما يجعله مستقرًا نسبيًا وأقل عرضة للإصابة أثناء الحركة.
يضم العمود الفقري القطني خمس فقرات (من L1 إلى L5)، وجميعها قادرة على الحركة والانثناء بقدر لا بأس به. ولأن هذا الجزء من العمود الفقري يحمل أكبر قدر من الوزن ويتيح أكبر قدر من الحركة (مما يُجهد المكونات التشريحية)، فهو المنطقة الأكثر ارتباطًا بآلام الظهر. وقد تنجم آلام الساق والقدم عن مشكلات في أسفل الظهر.
العجز (أسفل العمود الفقري) عظم مثلثي الشكل يعمل قاعدةً للعمود الفقري ويُشكّل جزءًا من الحوض.
تُعدّ L5-S1 منطقة من العمود الفقري القطني معرّضة على نحو خاص للتنكّس وآلام الظهر. وتُشكّل أربع عظام صغيرة بارزة من العجز العُصعص (coccyx)، أو عظم الذيل (العظم الذيلي في أدنى نقطة من العمود الفقري).
الميكانيكا الحيوية الفقرية في القطعة الحركية الفقرية لأسفل الظهر
يلتقي العمود الفقري القطني والعمود الفقري العجزي عند القطعة الحركية الفقرية L5-S1، المعروفة أيضًا بالمفصل القطني العجزي (lumbosacral joint). وهنا يتحول انحناء العمود الفقري من انحناء أمامي إلى انحناء خلفي (الانحناء الخلفي). وتُدعم الساقان والحوض بقدرة L5-S1 على نقل الإجهادات من العمود الفقري.
وبسبب بنيتها الفريدة والإجهاد الميكانيكي والضغوط الأكبر التي تتعرض لها مقارنةً بالقطع التي تعلوها، فإن القطعة الحركية L5-S1 تتعرّض للإصابة أكثر من غيرها. وقد تحدث الإصابات الرضّية، والتنكّس، وانفتاق القرص (disc herniation)، و/أو تهيّج الأعصاب بسبب هذه السمات.
المفصل L5-S1 كثيرًا ما يواجه مشكلات
كثيرًا ما تكون L5-S1 عرضة لإجهاد ميكانيكي حيوي مفرط، مما ينتج عنه إجهادات إضافية وزيادة في خطر الإصابة.. وهناك عدد من المشكلات الشائعة، منها
مشكلات الأقراص: توجد مشكلات تتعلق بالأقراص. فـ L5-S1 موضع شائع لانفتاق القرص في أسفل الظهر. ويتميّز هذا القرص بميل أشد انحدارًا، مما يزيد خطر الضرر والتنكّس نتيجة ازدياد قوى القصّ (shear forces).
مشكلة المفاصل الوجيهية (Facet Joint): ألم في المفاصل الوجيهية. فقد يتطور التهاب المفاصل الناتج عن البلى والاهتراء (الفُصال العظمي (osteoarthritis)) في المفصل القطني العجزي بسبب قدرته العالية على تحمّل الأحمال. كما قد تُسبّب الاضطرابات الالتهابية، مثل التهاب المفاصل الروماتويدي أو انزلاق الفقار التنكّسي، انزعاجًا في المفاصل الوجيهية.
انحلال الفقار (Spondylolysis). قد يُسبّب الإجهاد المتكرر انحلال الفقار، وهو كسر في الجزء بين المفصلي (pars interarticularis) (قطعة عظمية صغيرة تصل بين المفاصل الوجيهية للقوس الفقري) في الفقرة L5. وقد يحدث في أيٍّ من الجانبين. ويُطلق على الحالة التي لا ينكسر فيها العظم لكنه يتعرّض للإجهاد اسم «استجابة الإجهاد في الجزء بين المفصلي»، ويُشار إليها بتفاعل الإجهاد في الجزء بين المفصلي (pars stress reaction).
انزلاق الفقار (Spondylolisthesis). يحدث انزلاق الفقار عندما ينكسر الجزء بين المفصلي للفقرة L5 في الجانبين كليهما، مما يجعل الفقرة تنزلق فوق S1. وينجم انزلاق الفقار في L5 غالبًا عن الإجهاد المتكرر على الجزء بين المفصلي، ويُلاحظ أكثر ما يُلاحظ لدى الأطفال والمراهقين.. أما كسر الجزء بين المفصلي الناجم عن الرضّ فنادر جدًا.
ألم العصب الوركي والمفصل العجزي الحرقفي (SI): الأسباب الجذرية
قد يكون من الصعب تحديد المصدر الدقيق لانزعاج المريض. فقد ينجم ألم الظهر عن انضغاط الأعصاب في العمود الفقري، وكذلك عن اختلال وظيفة المفصل العجزي الحرقفي.
مشكلات العمود الفقري التي قد تؤدي إلى عرق النسا (sciatica)
1. انتفاخ القرص أو تمزّقه أو انفتاقه.
2. تضيّق القناة الشوكية (spinal stenosis)، وهو تضيّق القناة المركزية للعمود الفقري،
3. وهي حالة تضيق فيها الثقوب التي تخرج منها الأعصاب من العمود الفقري.
4. عندما تنزلق إحدى فقرات أسفل الظهر إلى الأمام، تُعرف الحالة بانزلاق الفقار (أو عدم الثبات القطعي).
5. حالة يتآكل فيها الغضروف بين المفاصل الوجيهية في الجزء الخلفي من العمود الفقري، مما يؤدي إلى اعتلال المفاصل الوجيهية (facet arthropathy).
6. جرح أو عدوى
7.أمراض ناجمة عن سوء التغذية والعوامل الوراثية (أقل شيوعًا)
الأسباب المحتملة لاختلال وظيفة المفصل العجزي الحرقفي
1. إصابات المفصل العجزي الحرقفي الناتجة عن السقوط أو حوادث السيارات أو الولادة، وكلها أمثلة على رضوض المفصل العجزي الحرقفي.
2. تنكّس المفصل العجزي الحرقفي
يمكن أن تكون كلتا الحالتين إما حادة (تستمر أقل من شهر) أو مزمنة (تستمر أكثر من شهر) (تستمر مدة طويلة جدًا).
قد يستغرق الأمر سنوات حتى يُشخَّص الأشخاص المصابون باختلال وظيفة المفصل العجزي الحرقفي ويُعالَجوا من آلامهم، التي قد تكون مُقعِدة.
وعندما يستمر الانزعاج أكثر من بضعة أسابيع أو يؤثر في أنشطتك اليومية، ينبغي لك استشارة الطبيب فورًا.
علاجات مميّزة
يُستخدم مصطلحا الطب البديل والطب التكميلي لوصف العلاجات غير الدوائية. ولا تعني كلمة «بديل» بالضرورة الدونية، بل تعني الخروج عمّا يُعدّ «تقليديًا» في الطب الغربي.
ثبت أن العلاجات البديلة لآلام أسفل الظهر تُساعد كثيرًا من الناس. ومن أكثر الخيارات شيوعًا:
المعالجة اليدوية. يُجري مقوّم العمود الفقري (chiropractor) أو ممارس رعاية صحية آخر تعديلات جسدية على العمود الفقري بهدف تحسين الحركة وتقليل التيبّس أو الانزعاج أو الألم. ويتم ذلك باستخدام دفعات يدوية متفاوتة السرعة والقوة. وقد خفّفت المعالجة اليدوية انزعاج أسفل الظهر لدى بعض الأشخاص.
الوخز بالإبر. يستند الوخز بالإبر إلى الطب الصيني التقليدي، ويستخدم مواضع في الجسم يُفترض أنها تُصحّح «التشي» (qi)، أي طاقة الحياة في الجسم. ويُقال وفقًا للطب الصيني إن التشي السليم يُخفّف الألم والمعاناة في الجسم. وتُغرز إبر دقيقة في الجلد لمدة تقارب الساعة. وقد ثبت أن الوخز بالإبر قد يُقلّل الألم تقليلًا ملحوظًا لدى بعض المرضى.
التدليك العلاجي. يُساعد التدليك العلاجي لأسفل الظهر على تخفيف التشنجات العضلية المسببة لانزعاج أسفل الظهر. وقد يُخفَّف ألم أسفل الظهر بزيادة تدفق الدم، الذي يحمل المغذيات والأكسجين إلى المنطقة للمساعدة في التعافي.
التأمل الواعي (Mindful meditation): التأمل بأسلوب هادئ ومتّزن. قد يُساعد التأمل على تخفيف أعراض الألم المزمن، مثل الحزن والقلق واضطرابات النوم. وتشمل العلاجات التأملية لتسكين الألم كل شيء بدءًا من تمارين التنفس العميق وصولًا إلى صرف التركيز بعيدًا عن الانزعاج.
روابط لبعض الأبحاث المتعلقة بتنكّس الأقراص المرتبط بآلام الظهر
- Low Back Pain: A Biomechanical Rationale Based on “Patterns” of Disc Degeneration.Von Forell GA, et al. Spine (Phila Pa 1976). 2015. PMID: 25996532
- Obesity is associated with reduced disc height in the lumbar spine but not at the lumbosacral junction.Urquhart DM, et al. Spine (Phila Pa 1976). 2014. PMID: 24825160
- [Advances in the study of anatomy and biomechanics of lumbosacral transitional vertebrae].Huang QQ, et al. Zhonghua Wai Ke Za Zhi. 2019. PMID: 30704219 Review. Chinese.
- Influence of age on the development of pathology.Sizer PS, et al. Curr Rev Pain. 2000.PMID: 10998745 Review.
- The segment-dependent changes in lumbar intervertebral …